Kimedics platform
Explore the platform
See how healthcare organizations move from reactive coverage to one connected clinician workforce operation. Tell us where to send the overview.
Kimedics is the clinician workforce operations platform built by healthcare operators. There is no list price, because a 40-clinician group and a 400-clinician health system are not running the same operation. Pricing follows the size of the workforce you run and the parts of the workflow you turn on.
Every quote comes down to the same three questions. There is nothing held back for later in a sales process.
How many clinicians you onboard, schedule and pay through Kimedics. This is the main driver, and it is the first thing we ask about.
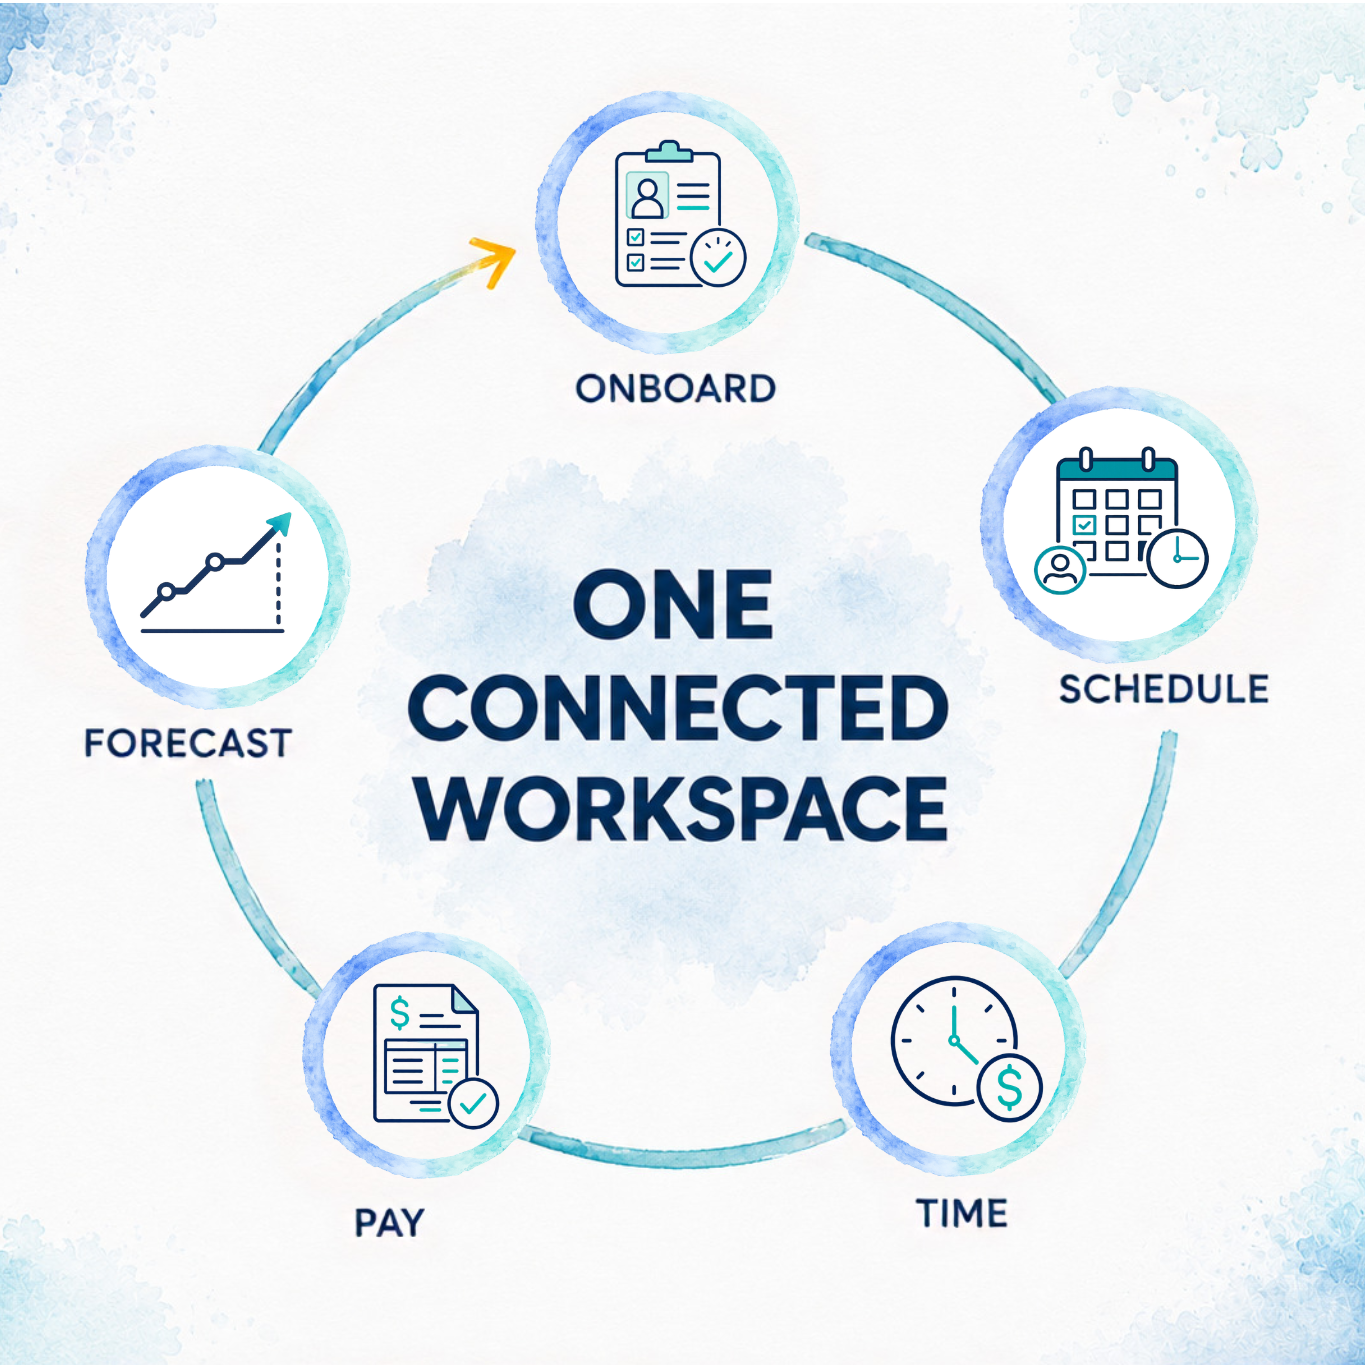
Onboarding and credentialing, scheduling, time and pay, billing and invoicing, forecasting and reporting. Most operations start with the part that is causing the most trouble and connect the rest as they go.
Bringing staffing partners onto the same workflow changes the shape of a deployment. Health systems and staffing organizations both run on Kimedics, and connecting the two sides is worth raising early rather than late.
Every organization on Kimedics runs the same platform. What changes is how much of it you have turned on, and where your operation cannot see clearly yet. That is what the first call is for.
There is no list price. Pricing follows the size of the clinician workforce you run and which parts of the workflow you turn on. A 40-clinician group and a 400-clinician health system are not running the same operation and should not pay the same for it. A thirty-minute call is usually enough to put a real number in front of you.
Published tiers tend to describe the vendor more than the buyer. Two operations with the same clinician count can need very different things depending on how much external coverage they carry, how many partners they work with, and which parts of the workflow are already handled somewhere else. A quote against your real operation is more useful than a band you have to fit yourself into.
Pricing is driven by the size of the clinician workforce you run, not by how many schedulers or coordinators sit in front of it. Adding people to your operations team does not change what you pay.
Yes. Most operations start where the pain is, usually onboarding and credentialing or scheduling, and connect the rest over time. Nothing has to be turned on at once, and the parts you add later work against the same data as the parts you started with.
NOT DRAFTED. Needs a real answer from sales before this page publishes. Do not publish the page with this question unanswered, and do not quietly drop the question either. It is the one people most expect to find here.
See how healthcare organizations move from reactive coverage to one connected clinician workforce operation. Tell us where to send the overview.